
Epidemiology
Femoral artery and external iliac artery two most common vascular injuries
Abularrage et al J Vasc Surg 2008
- incidence of vascular injury in 41,000 arthroplasty
- primary THA: 0.04%
- revision THA: 0.2%
Alshameeri et al Bone Joint J 2015
- systematic review of blood vessel injury during THA
- 55% primary THA
- common femoral artery most commonly injury via direct laceration
- external iliac vessels second most common
- death 8%
- amputation 2%
Mechanism of injury
Direct injury
| Blood vessel | Mechanism |
|---|---|
| Femoral artery |
Anterior retractors Anterior quadrant drills / screws |
| External iliac artery / vein |
Antero-superior screwss Revision of intra-pelvic components |
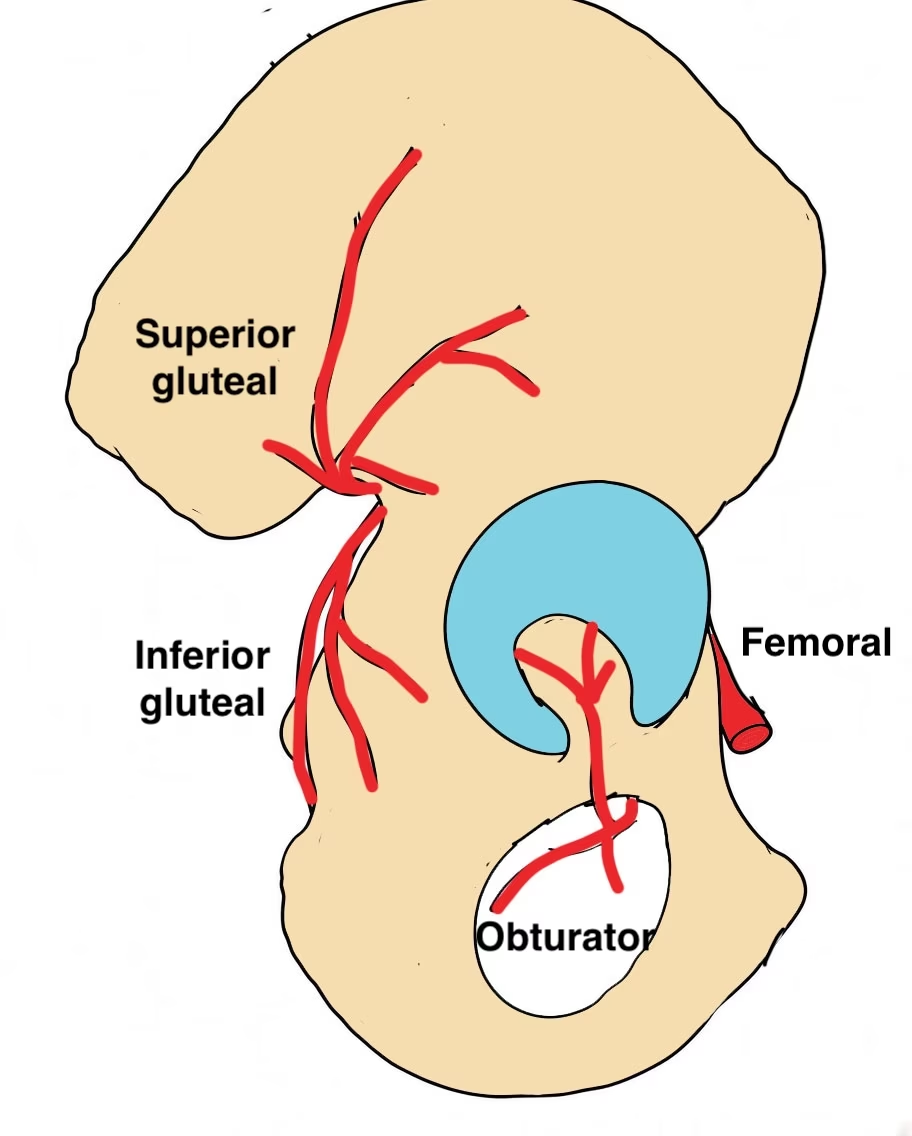
| Obturator artery |
Retractor transverse ligament Antero-inferior screws |
| Superior gluteal artery | Postero-superior screw into sciatic notch |
| Inferior gluteal artery | Postero-inferior screws |
Indirect injury
Arthrosclerotic vessels / thrombosis
- present with delayed ischemia
- angiography +/- thrombectomy
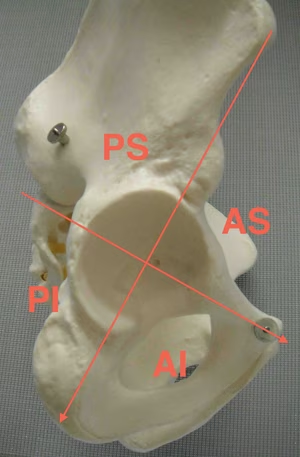
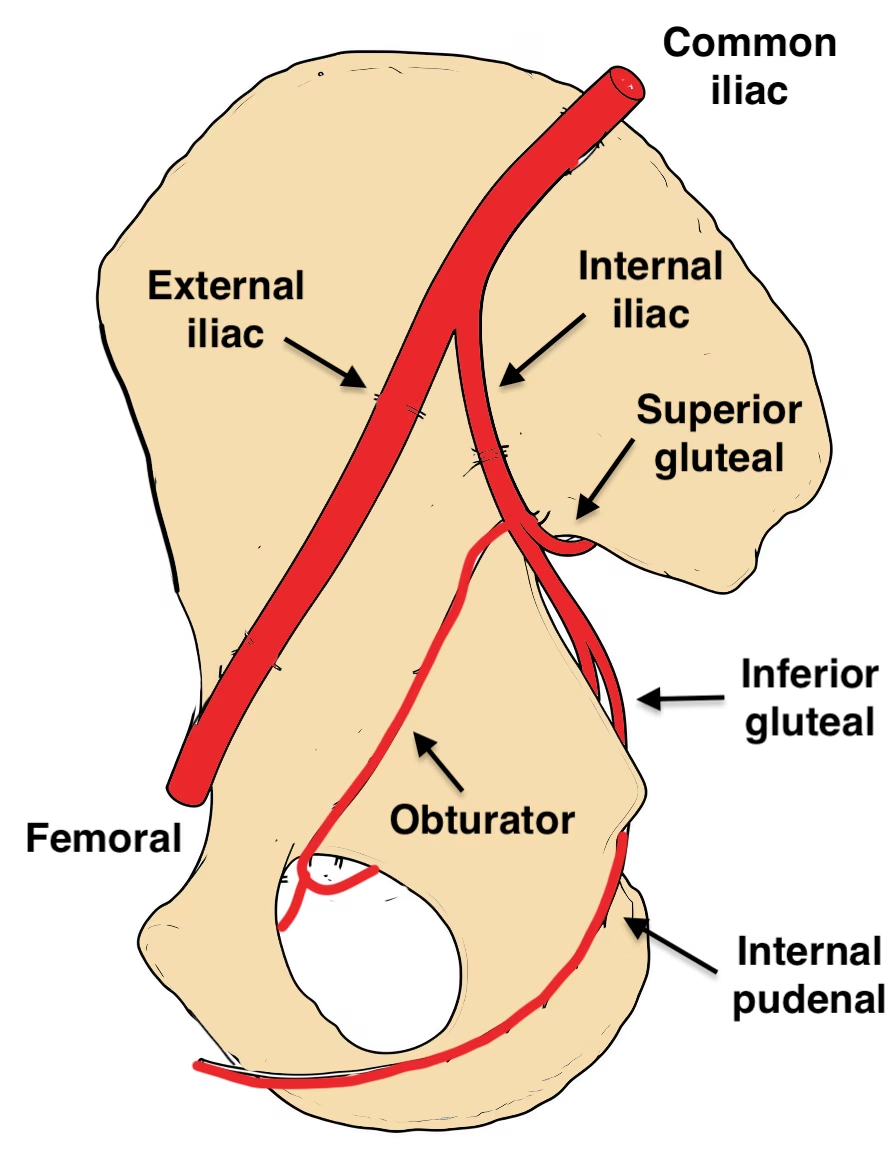
Safe zones acetabular screws
Presentation
Acute hemorrhage
Delayed bleeding / blood loss / hemodynamic instability - angiography
Ischemia - angiography
Pseudoaneurysm - angiography
Femoral blood vessels
Most commonly injured
Anatomy
Common femoral artery
- passes anterior to hip capsule
- separated from capsule by psoas
Danger
Anterior retractors / dissection
Anterior quadrant screws and drills
External iliac vessels
Anatomy
Commonly lie directly on bone of anterior acetabulum
Dangers
1. Anterosuperior screws
- vein more at risk than artery
- significant intrapelvic bleeding may occur before diagnosis
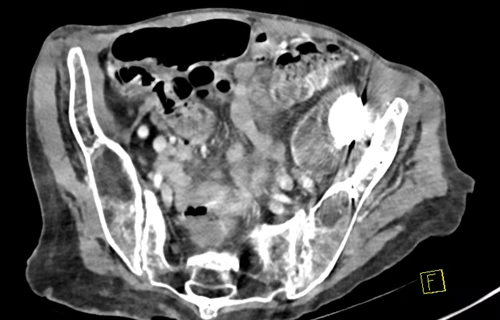
2. Revision of Intra-pelvic acetabular components
- CT angiogram pre-operatively
- may require separate intrapelvic exposure
- alert general surgeons / vascular surgeons

Obturator blood vessels
Anatomy
Traverse lateral wall
- separated from quadrilateral plate by obturator internus
- lie at superolater aspect of obturator foramen
- exit pelvis via obturator canal
Injury
Screws in anterior-inferior quadrant
Retractor under transverse acetabular ligament
Management
Bleeding at inferior transverse ligament
- can be very difficult to ligate
- pack with swab
- hold swab with inferior retractor
- finish acetabulum
- will usually be controlled
+/- embolization
Superor gluteal blood vessels
Anatomy
Branch posterior division internal iliac artery
- close to posterior column
- exits greater sciatic notch above piriformis
Injury
Screw near sciatic notch
Inferior gluteal & pnternal Pudendal vessels
Anatomy
Branch anterior division internal iliac
- exit pelvis between piriformis & coccygeus
- close to posterior column near ischial spine
- internal pudendal artery re-enters pelvis through lesser notch
- inferior gluteal artery passes under piriformis
Injury
Very long screws through posterior column
Management on table severe bleeding
Anaethetist
- IV fluids
- Bloods - coags, CBC, platelets, cross match
- transfuse blood +/- platelets
- organise cell saver
Control bleeding
- call vascular surgeon
- pack & wait
Vascular surgeon
- Ilioinguinal approach - clamp IIA, vessiloop IIV
- Retro-peritoneal approach / Rutherford-Morrison incision
Post-operatively
- angiography
- transcatheter embolisation